Quick answer
Can stem cells help knee osteoarthritis?
Mesenchymal stem cells (MSCs) may help some people with knee osteoarthritis, but the evidence is mixed and not definitive12. A 2025 meta-analysis of randomized trials reported improvements in pain and function1, while another review found that MSC therapy probably makes little or no difference to pain2. Researchers are still working out which cell source matters most13, and how many injections are optimal is still being studied4.
What is knee osteoarthritis and where do stem cells fit?
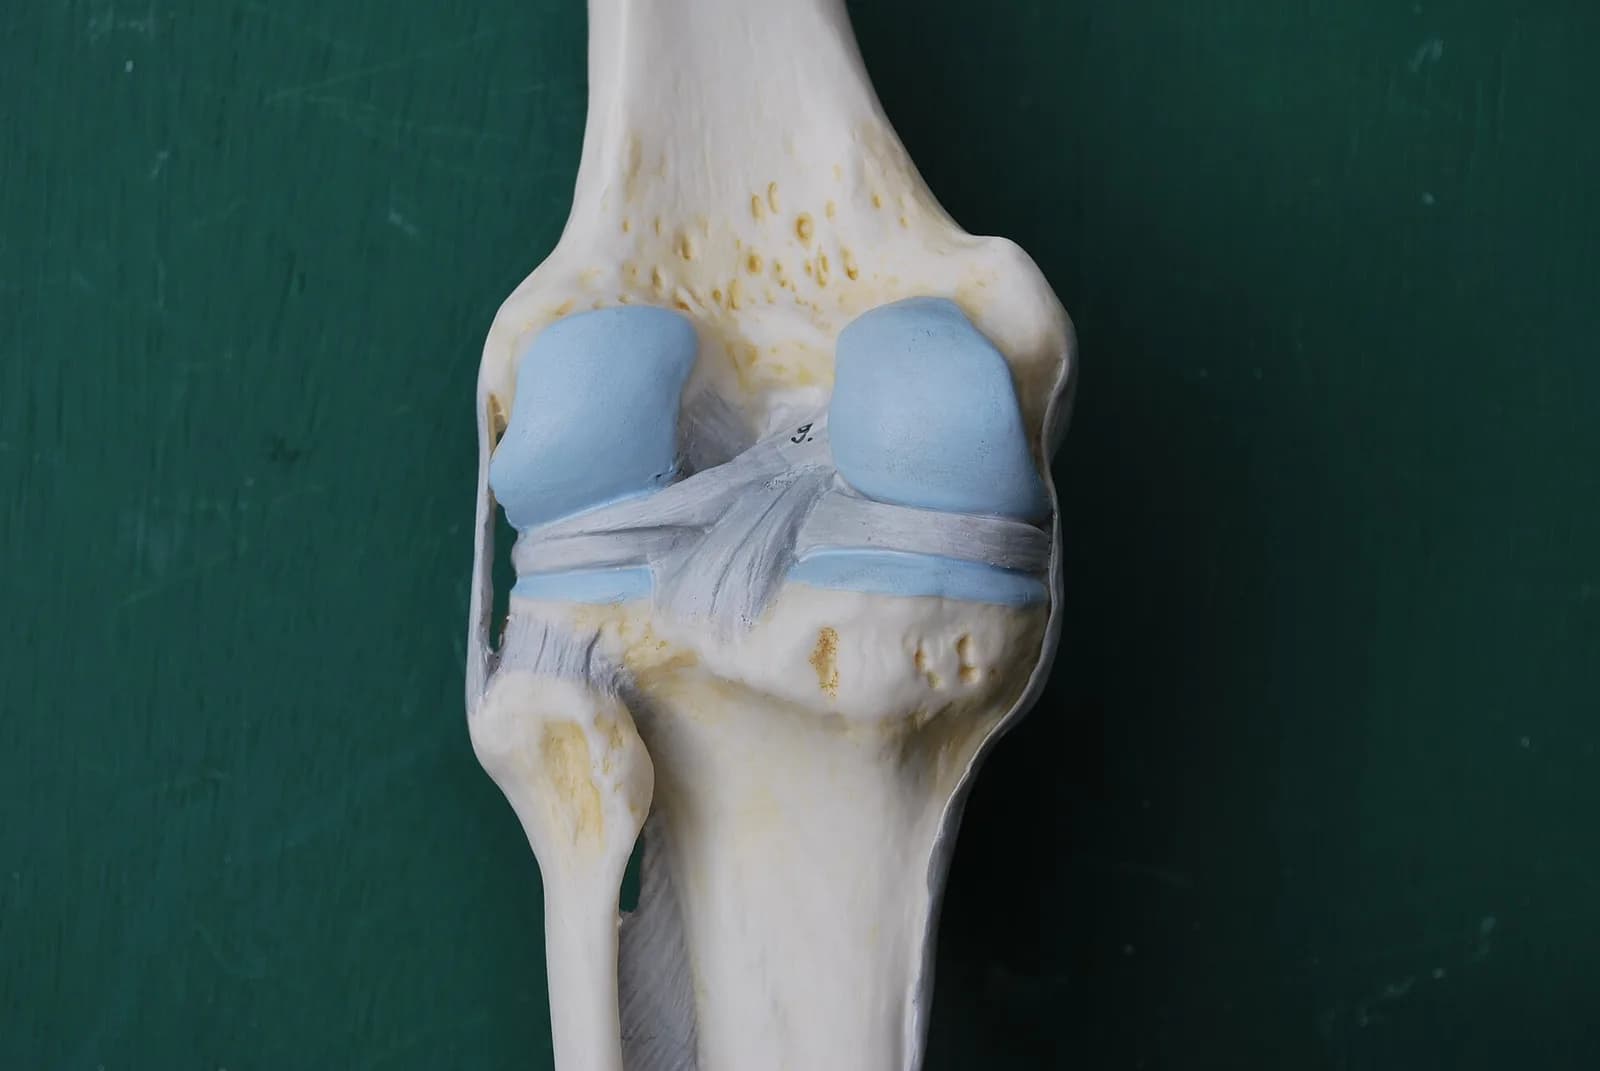
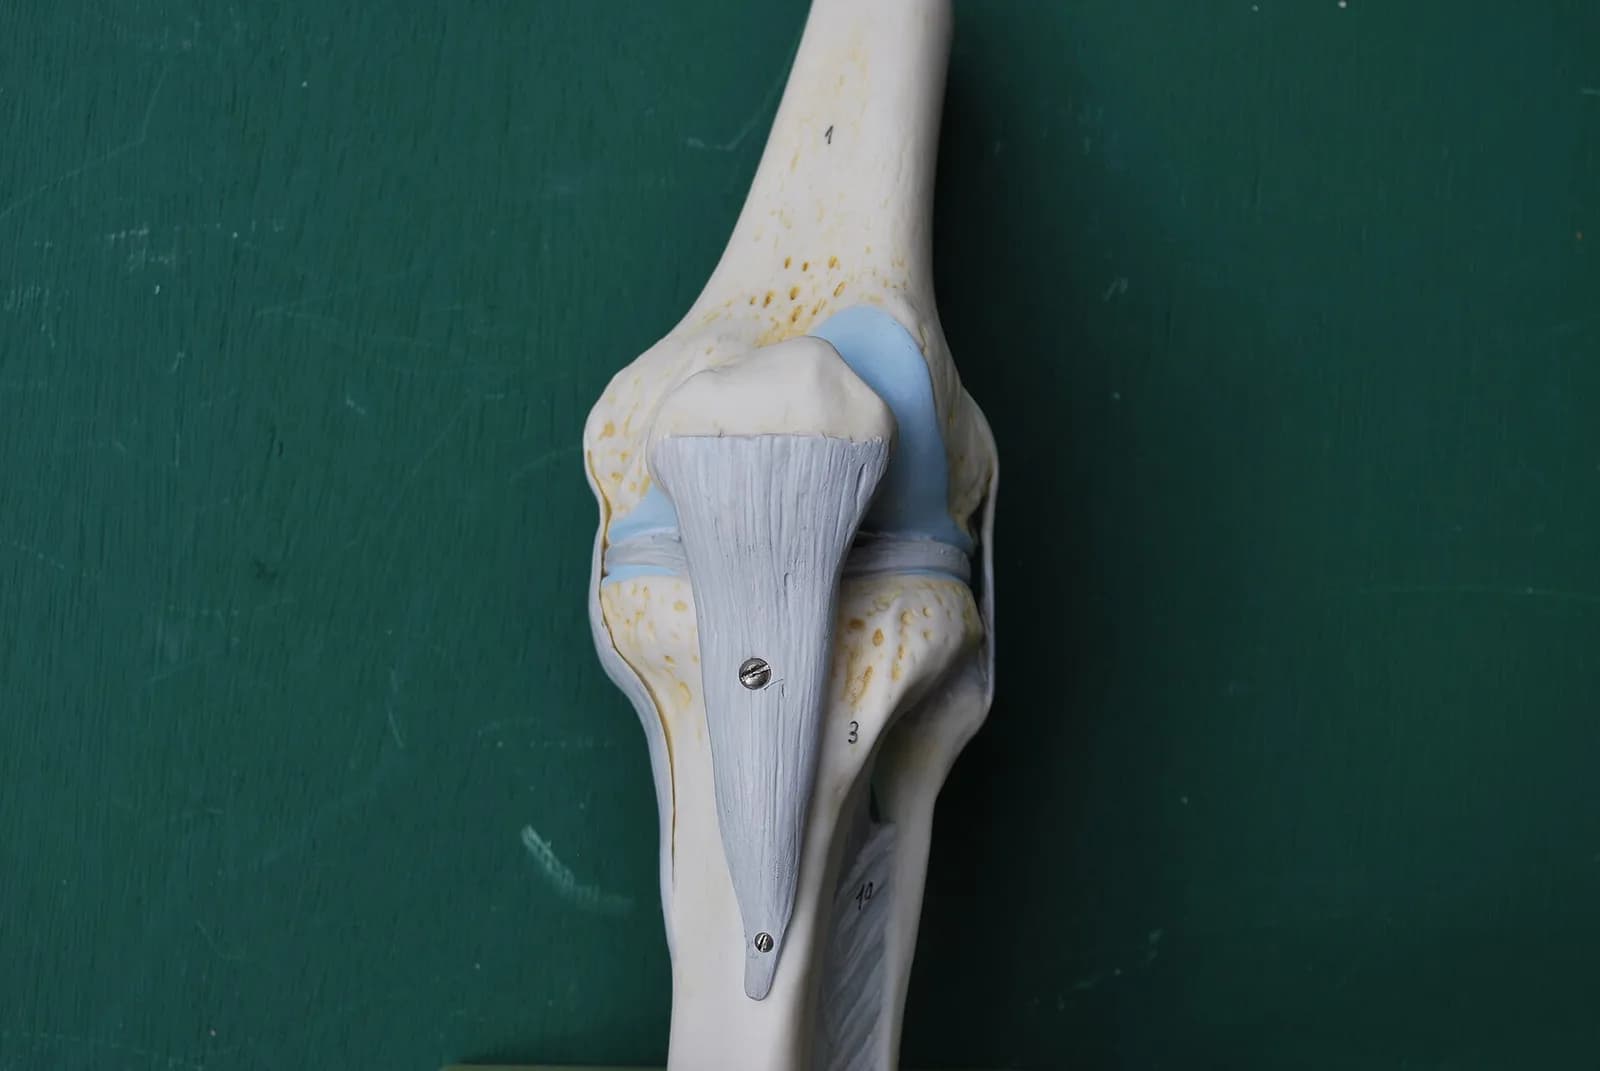
Knee osteoarthritis is a chronic joint condition that mainly involves progressive damage to articular cartilage and can later affect the subchondral bone and synovial structures3. Mesenchymal stem cells (MSCs) are being studied as a treatment option because they may influence inflammation and cartilage repair in the joint13.
In knee osteoarthritis, the inflammatory process is described as starting in the synovial membrane with activation of the immune system, and damage-associated molecular patterns play a role in that process3. The main 2025 review notes that MSCs are able to develop into chondrocytes under specific induction, a route the review links to articular cartilage repair1. Those authors also describe how MSCs release paracrine factors and extracellular vesicles that help regulate local inflammatory responses1. The same review also describes MSCs releasing growth factors and cytokines in the knee joint and mediating communication between cells1.
What types of stem cell injections are being studied?
The randomized trials in these reviews mainly test mesenchymal stem cells placed directly into the knee joint, and the cells come from more than one source1.
- Bone marrow-derived MSCs are one source described in the review1.
- Adipose tissue-derived MSCs are another source, and the 2025 meta-analysis reported more significant efficacy in the adipose-source subgroup1.
- Umbilical cord-derived MSCs are also discussed as a source in the review's background section1.
The delivery route in the main review was intra-articular injection for knee osteoarthritis, meaning the cells are placed into the knee joint itself rather than given systemically1. The review excluded trials that combined MSCs with platelet-rich plasma, bone marrow concentrate or surgical procedures, so its results describe MSCs alone1.
What does the research show about pain and function?
The results depend on which trials are pooled and which outcomes are measured12. In a 2025 meta-analysis of 8 randomized trials with 502 patients, MSC injections were associated with better WOMAC scores than control at 6 months, with a mean difference of 7.44 points, and at 12 months, with a mean difference of 10.31 points1. The same review reported improvements in visual analog scale (VAS) pain and Knee Injury and Osteoarthritis Outcome Score (KOOS) at 6 and 12 months1.
A 2024 review reached a more reserved conclusion after pooling 16 trials with 807 participants2. Its authors reported that, at 3-6 months, MSC therapy probably produces little or no change in pain, with a weighted mean difference of -0.74 cm on a 10-cm VAS2. At 12 months the review again found probably little or no difference in pain, with a weighted mean difference of -0.73 cm, while physical functioning may improve, with low certainty2.
A separate 2025 network meta-analysis of 16 trials with 622 patients also reported that MSC therapy improved pain and knee joint function at 3, 6 and 12 months4.
What did the phase III trial find?
A phase III, double-blind, placebo-controlled trial enrolled 261 patients with Kellgren-Lawrence grade 3 symptomatic knee osteoarthritis and gave them a single injection of autologous culture-expanded adipose-derived MSCs or placebo5. At 6 months, the adipose-derived MSC group showed greater improvement in 100-mm VAS pain scores (25.2 vs 15.5) and total WOMAC scores (21.7 vs 14.3) than the control group5. MRI showed no significant difference between groups in the change of cartilage defects at 6 months5. The authors called for long-term results to assess structural effects and to establish how long the effect of the injection persists5.
Why do studies reach different conclusions?
One part of the explanation lies in what each analysis allowed into its pool: the authors of the 2025 meta-analysis wrote that earlier reviews had included mixtures of MSCs with other components and studies that added surgical treatments, which interfered with judging the effect of MSCs alone1.
| Report | Participants or trials | Main finding | Source |
|---|---|---|---|
| Cao et al., 2025 | 8 trials; 502 patients | Better WOMAC scores at 6 and 12 months | 1 |
| Sadeghirad et al., 2024 | 16 trials; 807 participants | Little or no pain difference; possible physical function improvement at 12 months | 2 |
| Deng et al., 2025 | 16 trials; 622 patients | Single and repeated MSC injections may improve pain and function | 4 |
| Kim et al., 2023 | 261 patients | Greater VAS and WOMAC improvements than placebo at 6 months | 5 |
The 2024 review used GRADE to rate certainty and found moderate certainty for little or no pain difference at 3-6 months2. A 2023 review noted that many issues remain debated, including the best cell source and the nature of the cells3.
Injection frequency may also matter: the network meta-analysis of 16 trials with 622 patients found that repeated MSC injections were associated with greater improvements in pain and function at 6 and 12 months than single injections4.
What is still being studied?
Researchers are still trying to determine the best cell source, the ideal number of injections and whether MSC treatment changes the structure of the knee joint1354.
The phase III trial authors wrote that longer follow-up is needed to show whether the treatment modifies the disease, for instance by changing joint structure, and to establish how long its effect lasts5. The 2025 network meta-analysis called for large-scale, multicenter, long-term randomized trials to validate the approach further4. The 2023 review stated that further studies are needed to clarify the remaining doubts about MSCs in knee osteoarthritis3.
For now, the evidence supports a cautious description: MSC injections have shown promise for pain and function in some randomized trials and pooled analyses, but the size and certainty of the benefit vary132. Whether the treatment changes the structure of the joint has not been established5.
Frequently asked questions
How are stem cells given for knee osteoarthritis?
In the studies reviewed, mesenchymal stem cells were injected directly into the knee joint, a route called intra-articular injection1. The main meta-analysis included trials of MSCs alone, without surgery or platelet-rich plasma mixtures1.
Do stem cell injections rebuild knee cartilage?
The evidence does not show that they reliably rebuild cartilage5. In a phase III trial, MRI found no significant difference in the change of cartilage defects between adipose-derived MSC injections and placebo at 6 months5. Long-term results are needed to assess structural effects5.
How long do the effects last?
The main review reported better WOMAC scores at 6 and 12 months after MSC injection1, but a phase III trial called for long-term results to determine how long the effect of intra-articular MSC injections lasts5.